


Healthcare has stopped debating whether new technology belongs in clinical and administrative workflows. The debate now is about which investments survive contact with a real hospital, a real budget cycle, and a real regulator.
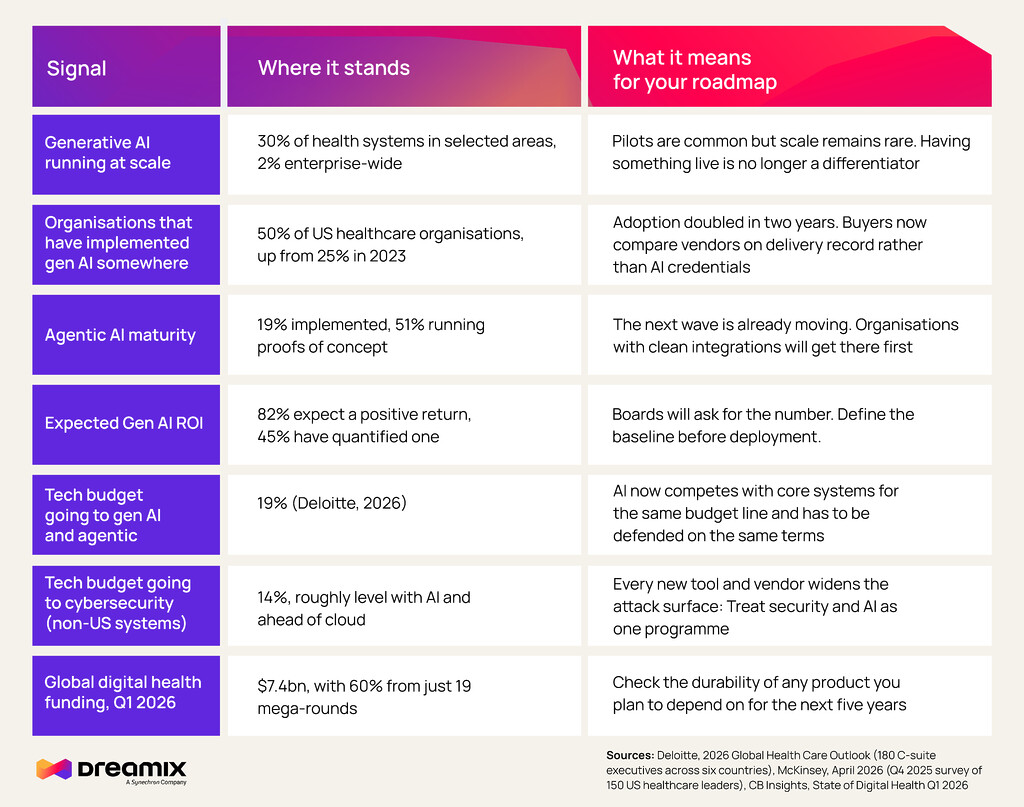
When it comes to innovations in healthcare, the debate is split. In McKinsey's fourth-quarter 2025 survey of US healthcare leaders, half of organisations reported they had implemented generative AI, up from 25% two years earlier. Yet Deloitte's 2026 Global Health Care Outlook, based on a survey of 180 C-suite executives across six countries, found only 2% of health systems running generative AI across the entire enterprise. Around 30% run it at scale in selected areas.
That gap between "we have it working somewhere" and "it changes how we operate" is where the real work in 2026 sits. This article looks at what is producing durable results in healthcare right now, what is blocking the rest, and how leadership teams should think about building versus buying when it comes to custom healthcare software development.
Innovation now competes on margin
Financial pressure is the organising principle of the 2026 healthcare agenda. Deloitte found that around 70% of non-US health system executives expect operating revenue and margins to rise, and more than half expect operating costs to stay flat or fall slightly. Those two expectations only reconcile through productivity.
When asked where savings would come from, executives pointed to three technology levers:
- Workflow standardisation and automation, cited by 64% of respondents. This is the least glamorous and most reliable category: intake, scheduling, coding, claims, prior authorisation, referral management.
- Predictive analytics for workforce planning, cited by 55%. Staffing is the single largest cost line in most systems, and rostering decisions made a week in advance are worth more than any dashboard produced a month later.
- Tech-enabled patient engagement and remote monitoring, cited by 49%.
McKinsey's survey points the same direction. Administrative efficiency was the domain most frequently named as having the greatest potential for both generative AI and multi-agent workflows with a Human in the Loop. For healthcare delivery organisations specifically, clinical productivity was the most widely implemented use case, with 54% reporting deployment.
The business translation for a CFO or COO: the projects paying back today are the ones that remove hours from a repeatable process, not the ones that promise a new diagnostic frontier. Frontier work matters, and it belongs on a longer horizon with a different funding logic.
Healthcare innovation in 2026: the numbers that matter
The workforce case is stronger than the technology case
More than 90% of the executives Deloitte surveyed named productivity improvement a priority for 2026, and workforce challenges ranked as their top concern overall. The World Health Organization projects a shortage of 4.5 million nurses by 2030. In the UK, 40% of general practitioners expect to leave the profession within five years.
This changes how a digital investment should be justified. A documentation tool that saves a clinician forty minutes a day is not primarily a cost-saving tool. It is a retention tool, and retention is where the money is. Replacing an experienced clinician costs far more than the licence fee on the software that might have kept them.
Deloitte's guidance for health systems includes offshoring IT and administrative work to relieve pressure on in-house teams, and it specifically names Eastern Europe as a common destination given the depth of its engineering talent and cost structure. The same report notes the constraint that goes with it: some jurisdictions, the UK among them, prohibit offshoring patient-level data. That is a design requirement, not a dealbreaker, and it needs to sit in the architecture from day one rather than surface during a security review.
Agentic AI is where the next round of value sits
Generative AI produces content and supports individual tasks. Agentic AI takes actions and coordinates processes end to end. That distinction is starting to show up in deployment data.
McKinsey found 19% of healthcare organisations have implemented agentic AI, with a further 51% running proofs of concept and just 1% reporting no plans at all. Adoption patterns vary by segment: care delivery organisations lean toward function-specific agents suited to particular clinical workflows, payers pursue end-to-end automation of standardised processes, and health services and technology firms build cross-cutting capabilities they can reuse across customers.
McKinsey's cross-industry research is blunt about which approach wins. High performers organise agentic AI around a complete workflow rather than around isolated functions or scattered use cases. A patient intake agent that handles verification, scheduling, records retrieval, and pre-visit communication as one chain produces more value than four separate tools that each handle one step and hand off through a human.
For technology leaders, the implication is architectural. Agents need reliable access to systems of record, clear permission boundaries, an audit trail, and a fallback path when they fail. Health systems running on fragmented data and undocumented integrations will find that agentic AI exposes every seam they have been working around.
Read next: Agentic AI vs Generative AI: Strategic Decision-Making for Enterprise Leaders
Three constraints decide whether an innovation sticks
1. Integration, which has overtaken risk as the main barrier
McKinsey's latest survey shows integration challenges now rank as the single most-cited obstacle to scaling generative AI, ahead of risk and safety concerns at 43%, with a lack of internal capability third. That reordering is a maturity signal. Once an organisation moves past planning, the hard part becomes embedding new tools into legacy clinical systems where orchestration and workflow redesign do the heavy lifting.
This is where legacy system modernisation and API integration work stop being back-office concerns and become the gating factor on an entire AI programme.
2. Regulation, which is now a design input
The EU AI Act has been in force since August 1, 2024 but its obligations will be phasing in throughout 2027 and the years to come. As Deloitte summarises, it requires nearly all AI-enabled medical devices, diagnostic algorithms, and clinical decision-support tools to go through mandatory risk management review. Regulatory uncertainty is one of the reasons adoption has moved more slowly on the clinical side than the administrative side.
For any organisation building or buying clinical AI in Europe, classification, documentation, human oversight, and post-market monitoring belong in the initial scope. Retrofitting them after a system is live costs several times more than designing for them.
Read next: EU AI Act: What It Is, Deadlines and How to Prepare in 2026
3. Cybersecurity, which now carries a budget line comparable to AI
Nearly half of non-US health executives (48%) named cybersecurity and data privacy a top concern for 2026, and they expect around 14% of technology budgets to go toward it. That puts cyber spending roughly on par with generative AI and digital health platforms, and ahead of cloud computing.
The economics explain the priority. Deloitte's 2026 midyear outlook notes that a medical record can sell for as much as $1,000 on the dark web, against $1 to $3 for an email login. Every new connected device and third-party vendor widens the attack surface, which means an AI programme and a security programme are the same programme. Which brings us to the next option.
Sustainability has two meanings, and both are now measurable
The original version of this article used "sustainable" to mean lasting. That still holds, and the financial evidence supports it. Among healthcare leaders who have implemented generative AI, McKinsey reports 82% expect a positive return, and 45% have quantified it, the highest share since the survey began. Reported returns run from under two times to four times the initial investment. Deloitte's picture is more cautious: 51% of its respondents either have not measured returns or consider it too early to tell, while 31% report moderate financial returns.
Both readings can be true. Organisations measuring carefully at the workflow level tend to see returns. Organisations measuring at the enterprise level, where a handful of pilots gets diluted across a full P&L, tend to see nothing yet.
The environmental meaning of sustainability is also now on the agenda, though unevenly. Deloitte's 2025 Global Health Care Outlook reported that the global healthcare sector produces up to 5.2% of the world's greenhouse gas emissions, while only 10% of surveyed health system executives were prioritising climate, even though 46% expected it to have a moderate impact on their organisation.
For technology teams, the overlap between the two definitions is practical. Shifting care to lower-cost settings reduces both cost and travel emissions. Virtual consultations remove journeys. Efficient cloud architecture and workload scheduling reduce compute cost and energy draw at the same time. Deloitte's recommended direction for 2026, moving care from hospitals toward homes and community settings through virtual care and remote monitoring, serves both goals without needing a separate business case.
Capability sourcing options for healthcare companies
Three options remain, and the trade-offs have shifted since this article was first published.
Build in-house. Viable for organisations with the scale to sustain a permanent engineering function. McKinsey's data shows a clear split: 36% of health services and technology firms report willingness to build in-house, compared with 19% of care organisations and 12% of payers. Care providers and payers rarely have software development as a core competency, and maintaining a senior engineering team for a non-core function is expensive in salary, recruitment, and opportunity cost.
Buy off-the-shelf. The fastest route to a working tool, and it is gaining ground. McKinsey found 33% of respondents pursuing a buy strategy in Q4 2025, up from 19% a year earlier, with 36% of care organisations and 39% of payers considering packaged solutions. McKinsey reads that as either a wish to move quickly or limited access to the internal capability needed to build. The limitation is unchanged: packaged solutions cover the use cases the vendor chose to cover, and healthcare workflows differ meaningfully between organisations. Where a product does not fit the process, the process usually bends, and clinical staff pay for that.
Partner with a specialist vendor. This remains the prevalent strategy across every subsector in McKinsey's survey. It gives an organisation senior engineering capacity without permanent headcount, and it keeps ownership of the resulting software with the health system rather than a licensor.
Next: Read more on the build vs buy vs partner decision when it comes to business software in our article by our CTO Denis Danov.
The selection criteria have tightened. Since integration is now the primary barrier, domain evidence matters more than technology credentials. A partner should be able to show relevant healthcare or regulated-industry delivery, familiarity with the compliance regime that applies, and a working approach to legacy environments.
Vendor durability deserves its own line in the evaluation. CB Insights reported $7.4bn in global digital health funding in Q1 2026, the highest quarterly total since Q2 2022, with mega-rounds accounting for 60% of it across just 19 deals. Capital pooling at the top means thinner funding for everyone below it, and the point solutions in that tier are the ones most likely to be acquired, repriced, or wound down. A clinical workflow built on a product that disappears in year three becomes a migration project nobody budgeted for. Ownership of the code and continuity of the team behind it are worth more in healthcare than in most sectors, because the switching cost lands on clinicians.
How Dreamix helps healthcare companies innovate
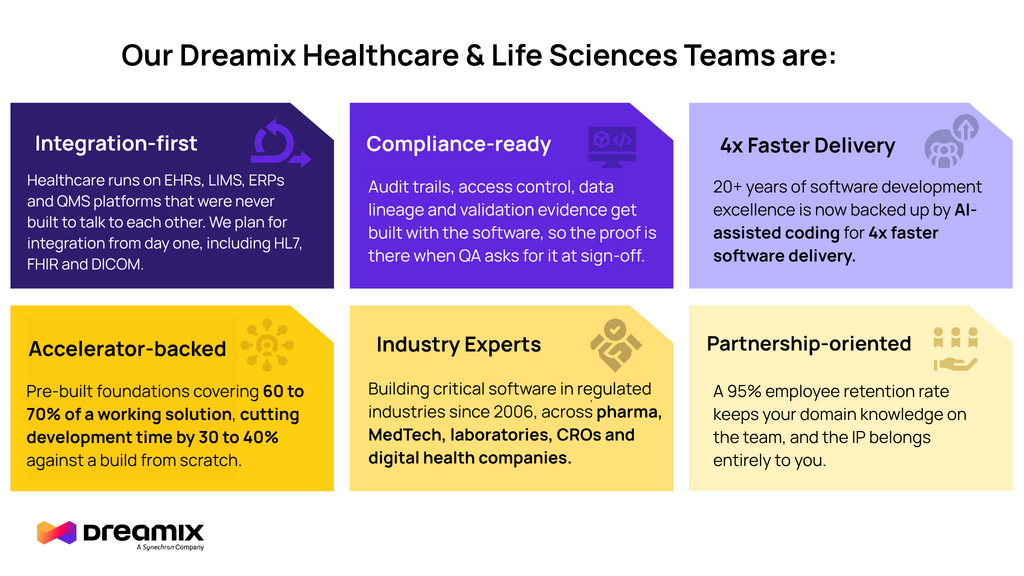
Connect the systems that block everything else. EHRs, LIMS, ERPs, QMS platforms and instruments were never designed to talk to each other. We plan integration from day one, including HL7, FHIR and DICOM, so new tools work inside your estate rather than beside it as another silo.
Move AI out of the pilot and into production. Most healthcare AI stalls on integration, validation and governance, not on the model. We do that work, so the thing that impressed people in a demo actually runs in front of real users.
Automate the work around clinicians. Fragmented workflows and repetitive admin consume scarce clinical capacity. Removing that friction gives teams more throughput without more headcount.
Start from something already built. Our medical accelerators such as the medical AI decision software cover 60 to 70% of a working solution and cut development time by 30 to 40%. Your budget goes into what is specific to your organisation, not into infrastructure that already exists.
Ship in weeks, not years. An accelerator customised, integrated and deployed in 60 to 90 days. A focused bespoke build live in 12 to 18 weeks. Complex programmes delivered in phases, each ending with something usable in production.
Build compliance in from the first architecture session. Audit trails, access control, data lineage and validation evidence produced alongside the software, across HIPAA, GDPR, GxP, 21 CFR Part 11, EU MDR, IVDR and the EU AI Act.
Keep the team, and the IP. The people who scope your project build it, and our 95% retention rate means your domain knowledge stays on it. The solution belongs entirely to you.
Practical next steps for the next 12 months
- Pick workflows, not tools: Map one end-to-end process, measure its current cost in hours and errors, then decide what technology belongs in it. Deloitte's advice on avoiding the pilot trap applies: if the business need is strong, start with a phase-one deployment designed to scale rather than a pilot designed to prove a point.
- Fund the integration layer before the AI layer: Interfaces, data quality, and identity management determine whether anything above them works.
- Put ROI measurement in the design: The organisations reporting quantified returns defined their baseline before deployment. Retrospective measurement rarely convinces a board.
- Assign cybersecurity ownership at executive level: Deloitte recommends treating it as a leadership responsibility rather than an IT function, given what a ransomware event does to both care delivery and public trust.
- Bring clinicians into design, not just into training: Deloitte highlights clinical entrepreneurship as a driver of adoption. Staff who helped shape a workflow defend it. Staff handed a finished tool work around it.
We’d love to hear about your healthcare software project and help you meet your business goals as soon as possible.


